The vaping products sold on this site are consumer products. They are not licensed medicines and they are not stop smoking treatments. Nothing here is medical advice or a claim about your health. If you smoke and want to stop, speak to your GP, pharmacist or local NHS stop smoking service about the licensed options available in the UK. These products are for adults aged 18 and over who already smoke or vape. If you have never smoked, do not start.
Ask about smoking and you are asking about one of the most thoroughly studied topics in medicine. Sir Richard Doll and Sir Austin Bradford Hill began the British Doctors Study in 1951 and followed its participants for fifty years. That evidence base is enormous, old and settled.
Ask about vaping and you are asking about a product category that only reached mass use in the 2010s. The studies exist, and some are large and well conducted, but they answer narrower questions over shorter periods. Most measure one of three things: what comes out of the device, what turns up in the blood and urine of people using it, or whether people who use it stop smoking. None of those is the same as knowing what happens to a person over forty years.
So when a headline tells you vaping is better or worse than smoking, the useful follow-up is always the same: better or worse at what, measured how, over how long, and compared with whom.
The Cochrane Library is an independent international network that produces systematic reviews of medical evidence. Its review “Electronic cigarettes for smoking cessation” was substantially updated in 2022, drawing on 78 studies and more than 22,000 participants.
Cochrane states that the review compared nicotine e-cigarettes with nicotine replacement therapy, with nicotine-free e-cigarettes, and with behavioural support or no support, and that its main outcome was smoking abstinence measured at six months or longer. The review also recorded reported adverse events in the included studies. Cochrane graded its own certainty for each comparison using the GRADE system, and the review is updated as new trials are published.
The review’s quit-rate figures, its plain-language summary and its certainty gradings are published on the Cochrane Library website, and anyone weighing them up should read them there in the authors’ own words rather than in a retailer’s paraphrase.
The second big strand of research looks at biomarkers: measurable chemicals in blood, saliva and urine that indicate what a person has been exposed to. OHID published an independent evidence update, “Nicotine vaping in England”, in 2022, led by Ann McNeill and colleagues at King’s College London. OHID found that, in the biomarker studies it reviewed, people who vaped and did not smoke had lower measured levels of certain biomarkers of exposure, including tobacco-specific nitrosamines and some volatile organic compounds, than people who smoked.
OHID also found that people who vaped and continued to smoke, described in the report as dual users, did not show the same reductions in measured biomarkers as people who had stopped smoking.
OHID states that a biomarker of exposure measures exposure to a substance and is not a measure of disease. That distinction is the one the report’s authors ask readers to keep in mind, and it is why this article reports exposure findings and disease findings separately.
| Type of study | What it measures | What it cannot tell you |
|---|---|---|
| Emissions analysis | Which compounds are present in aerosol produced in a lab | What a real person inhales, at their device settings and puffing pattern |
| Biomarker studies | Chemicals detectable in the body of a living participant | Whether that exposure level leads to disease decades later |
| Randomised trials | Whether an intervention changes behaviour over months | Long-term health outcomes, or results outside a supported trial setting |
| Observational cohorts | Patterns across large populations over time | Cause and effect, because the groups differ in many other ways |
| Systematic reviews | What the whole body of studies shows once pooled and graded | Anything the underlying studies never measured in the first place |
Every category above appears in the vaping literature. News reports rarely say which one they are quoting, which is why two accurate reports can appear to contradict each other.
Organisations that have reviewed broadly the same literature have published visibly different positions. Both are set out here in their own terms.
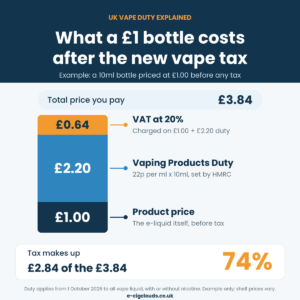
UK product rules are set out in the Tobacco and Related Products Regulations 2016, which our guide to UK vape law and regulations explains in plain terms, including the 10ml bottle limit, the 20mg/ml strength cap and the 2ml limit on nicotine-containing pods and tanks. Costs are changing too, as set out in our explainer on the new vape tax.
Popcorn lung. Cancer Research UK has published a fact check stating there have been no confirmed cases of the lung condition bronchiolitis obliterans caused by e-cigarettes. On the chemical at the centre of the claim, diacetyl, the regulations prohibit additive categories, and MHRA guidance treats diacetyl as unacceptable, so UK-notified nicotine liquids do not contain it.
The 2019 lung injury outbreak. The United States Centers for Disease Control and Prevention investigated the outbreak of lung injury it named EVALI and identified vitamin E acetate, used as a diluent in illicit THC-containing products, as strongly linked to the cases. The CDC states that most patients reported using THC-containing products obtained from informal sources.
Nicotine and cancer. Cancer Research UK states that nicotine is what makes tobacco addictive but that it is not the substance in cigarettes that causes cancer. The NHS states that nicotine is addictive, and advises anyone who is pregnant to speak to their midwife or GP.
Everyone is doing it. Action on Smoking and Health has run annual surveys of adult vaping in Great Britain for over a decade, and has consistently reported that the large majority of adult vapers are current or former smokers, with use among adults who have never smoked remaining low. ASH also publishes a separate annual survey of vaping among young people. The government’s stated reasons for banning single-use disposable vapes from 1 June 2025 included youth uptake and environmental waste. Prefilled pod kits and refillable kits are the formats sold legally in their place, as our prefilled pod kit buying guide sets out.
The bodies cited above name the gaps in the evidence themselves, and they are set out here.
Multi-decade outcomes. There is no forty-year cohort for vaping because vaping has not existed at scale for forty years. The strongest conclusions available today are about exposure and about behaviour, not about lifetime disease rates.
Flavourings inhaled over time. OHID identified inhaled flavourings as an area where further research is needed, noting that flavour compounds are generally assessed for use in food rather than for inhalation over long periods.
Device variation. Power, coil type, wicking and puffing behaviour all change what a device produces, which is one reason emissions studies disagree. The practical difference between styles is covered in our guide to MTL and DTL vaping.
Dependence patterns. How long people who vape continue to use nicotine, and whether they reduce or stop, is an area the research bodies named above continue to study.
If you already vape and want to understand the nicotine side better, our guide to how much nicotine to vape in the UK covers the 20mg/ml legal maximum and how strengths compare, and the strongest nic salt you can buy in the UK explains what that cap means in practice. For format questions, see shortfill versus 10ml e-liquid and the wider e-liquid range.
Cochrane Library, “Electronic cigarettes for smoking cessation”, 2022 update. Office for Health Improvement and Disparities, “Nicotine vaping in England”, independent evidence update, 2022, led by McNeill and colleagues. NHS guidance on vaping, nhs.uk. Cancer Research UK, including its published fact check on popcorn lung. Royal College of Physicians reports on tobacco and nicotine. World Health Organization statements on electronic nicotine delivery systems. United States Centers for Disease Control and Prevention investigation into EVALI. Action on Smoking and Health annual surveys of adult vaping in Great Britain. Tobacco and Related Products Regulations 2016.
Findings are summarised with attribution to the organisations that published them. Nothing here should be taken as a claim made by this retailer.
Free UK delivery over £15, 1.8 reward points on every £1 and 20,000+ five-star reviews. These guides cover the practical side of running a kit you already own: the law, the hardware and the strength table.
No. The NHS states on its own website that vaping is not risk free and that nicotine is addictive. Cancer Research UK notes that e-cigarettes have not been around long enough for their long-term effects to be fully known.
No product on this site is licensed as a stop smoking treatment, and this article makes no claim that one works as such. The Cochrane review and the OHID evidence update summarised above are the places to read what the trials measured and how the authors graded their own certainty.
Usually because they measured different things. An emissions study, a biomarker study and a randomised trial answer different questions, and the comparison group changes the result entirely. Check what was measured and against whom before deciding a study is an outlier.
Dual use means vaping while still smoking. Researchers report it as its own group because the exposure picture for someone who has replaced every cigarette is different from the picture for someone who has replaced only some of them, and pooling the two would blur both results. It is also why survey figures on how many people vape say little on their own about how many have stopped smoking.
Cancer Research UK has published a fact check stating there are no confirmed cases of the condition caused by e-cigarettes. The claims section above covers where the diacetyl story came from and how UK regulation handles that additive.
No. Single-use disposable vapes were banned from sale across the UK on 1 June 2025. Refillable pod kits (see our beginner pod kit guide) and prefilled pod kits are the legal replacements, and our complete guide to e-cigarettes, e-liquids and kits covers how they differ.